──── BLOG |
Virtual Reality in Healthcare Education
Virtual reality in healthcare education is not one thing. It covers rehearsing a procedure before performing it, learning equipment that is not in the room, and putting a clinician inside a situation that cannot safely be staged.
This guide covers what VR is genuinely good at in medical training, the applications that come up most often, the practical challenges nobody mentions in the demo, what it costs in effort rather than in money, and where the field is going.
What virtual reality adds to medical training
Three things a video cannot. Presence: the trainee is inside the scene and has to look around to find what matters, which is closer to the real task than watching a camera do the looking. Repetition without consequence: the same step can be attempted ten times, wrongly, at no risk. And measurement: an application knows what the trainee did, in what order, and where they hesitated.
That third one is the least discussed and often the most valuable. A video is watched; a simulation is performed, and performance can be reviewed.

The applications that come up most often
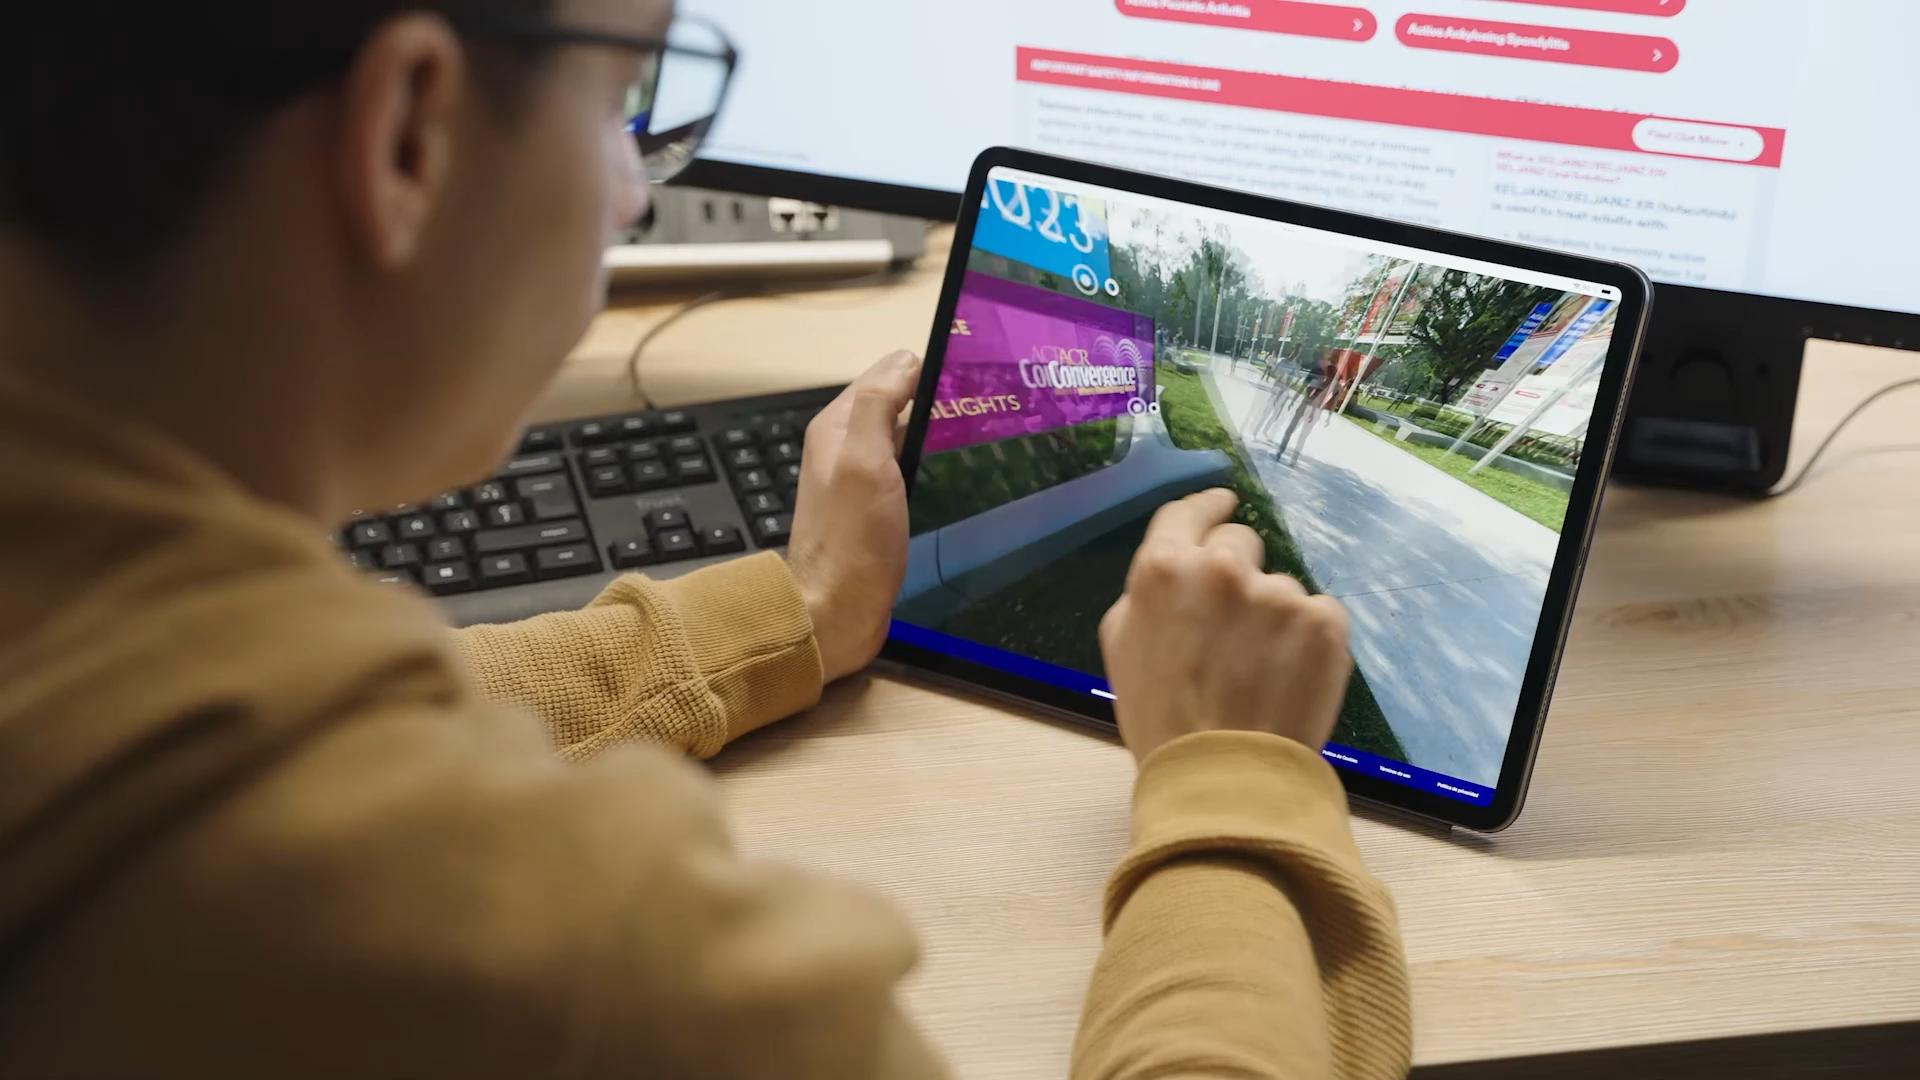
Procedure rehearsal, where the sequence and the decision points matter more than the scenery. Equipment training, where the problem is that the hardware cannot be shipped to every session — the problem Werfen set out to solve when it turned its training into an immersive, collaborative experience.
Environment familiarisation: theatres, labs, clean rooms, a congress space. And communication training, where the difficulty is the conversation rather than the technique.
Outside pure training, the same technology carries scientific content at events: the medical metaverse and virtual showroom we built for Zeiss Medical Technology is a teaching space as much as a commercial one.
The challenges nobody mentions in the demo
Headsets have to be managed: charged, updated, cleaned, and someone has to be in the room when twelve people put them on at once. Sessions are short, because comfort limits them, so the content has to be built for ten or fifteen minutes rather than an hour.
Content ages with the protocol. A VR module built around a procedure becomes wrong when the procedure changes, and updating it is not the same as editing a slide. That maintenance cost belongs in the business case from the start.
And the obvious one: if the learning objective is a fact, VR is an expensive way to deliver a fact.


What it costs in effort, not in money
The build is the visible cost. The invisible ones are the clinical review — someone qualified has to confirm that the simulated steps are the real ones — and the pilot, because a module that works on the developer’s machine behaves differently with a nervous trainee wearing the headset for the first time.
Budget for a pilot session and a revision round after it. Projects that skip that step ship something technically finished and pedagogically untested.
Where it is going
Two directions that are already visible. Standalone headsets that need no computer or external sensors, which is what makes group sessions practical outside a lab. And interactive applications that are not full VR — 3D on a tablet, or augmented reality over the real equipment — because for many training objectives they deliver most of the benefit with none of the hardware logistics.
The useful question is therefore rarely “should we do VR”. It is “what is the lightest format that achieves this learning objective”.

MORE GUIDES
VR for Pain Management: How It Is Used and What It Takes to Build
What Is VR Therapy? Uses, Limits and How One Is Built

3D Body and Face Scanning for Medical Projects: When It Is Worth It
Digital Human and Avatar Technology: How One Is Actually Built
What Is a Digital Human? Uses in Healthcare and Pharma
Virtual Reality in Psychology: What Is Used and What It Takes to Build
What Is a Virtual Patient? Uses in Medical Training

Scientific Infographic Examples for Research and Pharma

Augmented Reality in Surgery: Use Cases Today

VR Surgical Training: How It Works and What It Costs
Contact
Contact Us
Contact
Contact Us
Boston, Massachusetts, USA
T: (+1) 617 351 8477
M: (+1) 484 473 1704
info@pixel-medical-animation.com
Business Hours:
Mon-Fri: 9am-6pm (local time)
How can we help you?

SERVICES
- Medical 3D Animation in Boston
- Medical 3D Animation in Miami
- Medical 3D Animation in Los Angeles
- Medical 3D Animation in Minneapolis
- Medical 3D Animation in New York
- Medical 3D Animation in Raleigh Durham
- Medical 3D Animation in Chicago
- Medical 3D Animation in Texas
- Medical 3D Animation in Seattle
- Medical 3D Animation in Washington DC